Learning objectives and key messages
- After this lesson you should be able to manage the immune-related adverse events (irAEs) of checkpoint inhibitors by organ and grade, and know when to continue, hold or permanently stop the drug [1, 2].
- General rule: grade 1, continue treatment with monitoring; grade 2, hold and give corticosteroids if needed; grade 3, hold and give high-dose corticosteroids; grade 4, stop permanently (except endocrinopathies controlled with hormone replacement); taper corticosteroids over at least 4 to 6 weeks [1].
- Endocrinopathies are usually permanent but are controlled with hormone replacement, often without stopping immunotherapy; in hypophysitis or adrenal insufficiency, check cortisol before levothyroxine [2].
- Myocarditis is rare but the most fatal irAE (death in 39.7% of reported cases) and often occurs together with myositis and myasthenia; start methylprednisolone 1000 mg daily without delay [2, 3].
- After CAR-T and bispecific antibodies, grade CRS and ICANS with the ASTCT consensus criteria; tocilizumab is the key treatment for CRS but does not treat ICANS, where corticosteroids are the mainstay [4, 5].
- After CRS resolves, think of HLH-like syndrome (IEC-HS), prolonged or biphasic cytopenias (ICAHT), infections and late neurological toxicity (such as parkinsonism after anti-BCMA CAR-T) [6, 7, 8].
General principles of managing immune-related adverse events (irAEs)
Mechanism and timing. The same mechanism that produces the antitumour effect of immune checkpoint inhibitors (ICIs), namely the escape of autoreactive T cells from immune tolerance, causes much of the irAE burden. These events can occur at any time during treatment and even 6 to 12 months or more after it stops, and some (such as type 1 diabetes and thyroid destruction) are lifelong [2]. The 2021 ASCO and 2021 SITC guidelines organise management by the organ involved and the CTCAE grade, and because randomised trials are lacking, the recommendations rest mostly on expert consensus [1, 2]; the 2022 ESMO guideline also gives recommendations for the diagnosis, treatment and follow-up of immunotherapy toxicities [9].
Incidence and mortality. In the CheckMate 067 trial (melanoma), grade 3 or 4 treatment-related adverse events occurred in 16.3% with nivolumab, 27.3% with ipilimumab and 55.0% with nivolumab + ipilimumab [10]. In a meta-analysis of 112 trials (19,217 patients), toxic deaths were 0.36% with anti-PD-1, 0.38% with anti-PD-L1, 1.08% with anti-CTLA-4 and 1.23% with the combination; deaths occurred early (median 14.5 days with combination treatment and 40 days with monotherapy), and myocarditis had the highest fatality (39.7%), whereas colitis was the most common cause of death with anti-CTLA-4 and pneumonitis the most common with anti-PD-1/PD-L1 [3].
Before starting treatment. Baseline and periodic CBC, metabolic panel, TSH and free T4; urinalysis if kidney disease is suspected; in patients at high risk of myocarditis (heart disease, diabetes, anti-PD-(L)1 combined with anti-CTLA-4), consider a baseline ECG and troponin. Patient education about symptoms is essential; pre-existing autoimmune disease is not an absolute contraindication, but flares are common (about 50%) [2].
Treatment principles. Unlike chemotherapy, ICI dose reduction has no role in managing irAEs. Systemic corticosteroids are first-line treatment, and patients should be taught about their side effects (hyperglycaemia, mood disturbance, insomnia, gastritis and opportunistic infections such as pneumocystis); cases not responding to corticosteroids need a second-line immunosuppressant and specialist advice [2]. Before treatment, exclude other causes (for example Clostridioides difficile infection in diarrhoea), but do not delay starting treatment [2].
Rechallenge. After a grade 2 irAE, continuing the ICI is possible if symptoms have resolved or are controlled with prednisone 10 mg a day or less; after grade 3 or 4 the decision is based on the balance of benefit and risk. In two retrospective reviews, the previous irAE recurred after rechallenge in 43% and 26%, and a new irAE occurred in 13% and 26% [2].
| Grade | Action on the ICI | Corticosteroids and treatment |
|---|---|---|
| Grade 1 | Continue treatment with close monitoring (except some neurological, haematological and cardiac toxicities) | Usually not needed |
| Grade 2 | Hold for most toxicities; resume when symptoms return to grade 1 or less (and prednisone ≤10 mg a day) | Depending on the organ, corticosteroids (dose in the organ-specific table) |
| Grade 3 | Hold; rechallenge only after weighing benefit and risk | High-dose corticosteroids; taper over at least 4 to 6 weeks; in refractory cases, another immunosuppressant |
| Grade 4 | Stop permanently, except endocrinopathies controlled with hormone replacement | High-dose corticosteroids and second-line treatment in refractory cases |
Summarised from the 2021 ASCO and 2021 SITC guidelines [1, 2]. Exceptions: in myocarditis, myasthenia, Guillain-Barré syndrome and encephalitis, treatment is urgent and aggressive from a low grade.
Organ-specific management of irAEs (doses based on SITC 2021)
Treatment regimens and doses: index11 regimens
| Toxicity | Key assessment | Treatment by grade | Refractory cases and notes |
|---|---|---|---|
| Colitis and diarrhoea | Grade ≥2: faecal calprotectin, Clostridioides difficile and CMV; sigmoidoscopy or colonoscopy with biopsy for grade ≥3 or grade 2 for more than 5 days | Grade 2: prednisone 1 mg/kg/day; grades 3 and 4: 1 to 2 mg/kg/day (grade 4 initially IV); taper over 4 weeks after improvement to grade 1 | No response in 3 to 5 days or recurrence: infliximab 5 mg/kg at weeks 0, 2 and 6; if persistent after the second dose, vedolizumab [2] |
| Hepatitis | Liver enzymes before each infusion; grade ≥2: autoimmune and viral panel; grade ≥3, monitor every 1 to 2 days | Grade 2: prednisone 0.5 to 1 mg/kg/day; grades 3 and 4: methylprednisolone 1 to 2 mg/kg/day; taper over 4 to 6 weeks | No improvement in 10 to 14 days: mycophenolate; do not use infliximab because of hepatotoxicity [2] |
| Pneumonitis | High-resolution CT; with a negative CT, lung function tests with DLCO | Grade 2: prednisone 1 to 2 mg/kg/day; grade ≥3: IV methylprednisolone 1 to 2 mg/kg/day; taper over 4 to 6 weeks | No improvement in 72 hours: mycophenolate, IVIG, infliximab, cyclophosphamide or tocilizumab [2] |
| Rash | Percentage of body surface area, blisters and mucosal involvement; for grade ≥3, dermatology advice and biopsy | Topical or oral corticosteroids according to severity; blisters or mucosal involvement: hold the ICI until resolution and assess for SJS/TEN and bullous diseases | Recurrence after steroid taper: a steroid-sparing agent (rituximab in pemphigus, dupilumab in eczema) [2] |
| Hypo- or hyperthyroidism | TSH and free T4 every 4 to 6 weeks during treatment and every 6 to 12 months after it ends | Hypothyroidism: levothyroxine; symptomatic hyperthyroidism: a beta-blocker (cardioselective in asthma or COPD) | Corticosteroids are usually not needed; the ICI often continues [2] |
| Hypophysitis | Low TSH with normal or low free T4; ACTH and morning cortisol; then FSH, LH and sex hormones | Symptomatic acute hypophysitis: hold the ICI and give corticosteroids; then hydrocortisone replacement | Teach stress dosing and a medical alert bracelet [2] |
| Primary adrenal insufficiency | Morning cortisol, metabolic panel and ACTH stimulation test | Any grade: hold the ICI and replace steroids | Watch for signs of adrenal crisis; medical alert bracelet [2] |
| Type 1 diabetes | HbA1c, C-peptide and autoantibodies; check for ketoacidosis | Insulin; ketoacidosis or severe hyperglycaemia: admission and hold the ICI until ketoacidosis resolves | Corticosteroids have no role [2] |
| Myocarditis | Any cardiac symptom, arrhythmia, conduction block or raised troponin within 12 weeks of the ICI; cardiac MRI, ECG, troponin; admission | Methylprednisolone 1000 mg IV daily for 3 to 5 days (until troponin normalises), then prednisone 1 to 2 mg/kg tapered over 4 to 6 weeks; strongly consider permanent discontinuation of the ICI | No response in 24 hours: ATG, mycophenolate, abatacept or alemtuzumab; avoid infliximab; admission to a CCU with access to a temporary pacemaker [2] |
| Myasthenia gravis | Antibodies, concurrent assessment for myositis, myocarditis and thyroid; NIF and vital capacity | Grade 2: stop the ICI, prednisone 1 to 1.5 mg/kg/day and pyridostigmine; grades 3 and 4: admission (possibly ICU), permanent discontinuation, IVIG or plasmapheresis | Repeated assessment of respiratory function [2] |
| Encephalitis and Guillain-Barré syndrome | MRI, lumbar puncture, EMG and nerve conduction studies; exclude infection (empirical antivirals in encephalitis) | Any grade: methylprednisolone 1000 mg IV daily for 3 to 5 days plus IVIG or plasmapheresis | Guillain-Barré: stop the ICI permanently; refractory encephalitis: IVIG, plasmapheresis or rituximab [2] |
| Acute kidney injury (interstitial nephritis) | Urinalysis and protein-to-creatinine ratio; stop drugs that cause nephritis (NSAIDs, PPIs); strongly consider a kidney biopsy | Stage 1: hold the ICI and investigate; stages 2 and 3 or grade ≥2 proteinuria: hold and refer urgently to nephrology; glucocorticoids first line | Refractory nephritis: infliximab or mycophenolate [2] |
The table is based on the SITC 2021 recommendations; see the full guideline for details and levels of evidence [2].
Endocrinopathies: an important exception
In endocrinopathies, hormone replacement is the main treatment, and the ICI usually continues once the patient is stable, often without interruption; thyroiditis and type 1 diabetes usually do not need corticosteroids. In a patient with symptoms of hypothyroidism or a raised TSH and low free T4, check morning cortisol to exclude concurrent adrenal insufficiency [2]. The relative risk differs by regimen: in a meta-analysis of 38 trials (7551 patients), combination treatment compared with ipilimumab increased the risk of hypothyroidism (OR 3.81), hyperthyroidism (OR 4.27) and hypophysitis (OR 2.2), whereas PD-1 inhibitors compared with ipilimumab caused less hypophysitis (OR 0.29) but more hypothyroidism (OR 1.89) [11].
Myocarditis and the myositis–myocarditis–myasthenia triad
In a multicentre registry, the prevalence of myocarditis was 1.14% and the median time to onset 34 days after starting the ICI; 46% of patients had a major adverse cardiac event (cardiac death, cardiogenic shock, cardiac arrest or complete heart block), 38% of them with a normal ejection fraction. Combination ICI treatment (34% vs 2%) and diabetes were more common in affected patients, troponin T ≥1.5 ng/mL increased the risk fourfold, and lower corticosteroid doses were associated with higher residual troponin and more events [12]. Myositis, myocarditis and myasthenia often occur together (reported fatality 20% for myasthenia and 17% for myocarditis); so suspicion of any one should prompt assessment of all three (CK, troponin, ECG, myasthenia antibodies and respiratory assessment) [2].
Drugs for managing irAEs (doses as in SITC 2021)
Systemic corticosteroids (by organ and grade)
First line for most grade ≥2 irAEs (except endocrinopathies and diabetes)
First line for most grade ≥2 irAEs (except endocrinopathies and diabetes)
| Drug | Dose | Route | Schedule |
|---|---|---|---|
| Grade 2 | |||
| Prednisone | 0.5 to 1 mg/kg/day (hepatitis); 1 mg/kg/day (colitis); 1 to 2 mg/kg/day (pneumonitis) | Oral | Daily |
| Grades 3 and 4 | |||
| Methylprednisolone or prednisone | 1 to 2 mg/kg/day | IV (IV in grade 4 colitis and grade ≥3 pneumonitis) | Daily |
| Pulse | |||
| Methylprednisolone | 1000 mg | IV | Daily for 3 to 5 days (myocarditis, encephalitis, Guillain-Barré) |
Infliximab
Corticosteroid-refractory colitis (3 to 5 days), recurrent or with severe ulceration; refractory pneumonitis
Corticosteroid-refractory colitis (3 to 5 days), recurrent or with severe ulceration; refractory pneumonitis
| Drug | Dose | Route | Schedule |
|---|---|---|---|
| Colitis | |||
| Infliximab | 5 mg/kg | IV | Weeks 0, 2 and 6 |
| Pneumonitis | |||
| Infliximab | 5 mg/kg | IV | One dose; optional repeat after 14 days |
Check HBV, HIV and tuberculosis before infusion, but waiting for the results should not delay treatment; avoid or use with caution in ICI hepatitis because of the risk of hepatotoxicity, and in refractory myocarditis [2].
Vedolizumab
Colitis persisting after the second infliximab dose
Colitis persisting after the second infliximab dose
| Drug | Dose | Route | Schedule |
|---|---|---|---|
| Vedolizumab | 300 mg | IV | Weeks 0, 2 and 6 (the third infliximab dose is not given) |
As in SITC 2021; screen for HBV, HIV and tuberculosis before infusion [2].
Mycophenolate mofetil
Hepatitis not improving to grade 1 within 10 to 14 days or recurring after steroid taper; refractory pneumonitis; refractory myocarditis or nephritis
Hepatitis not improving to grade 1 within 10 to 14 days or recurring after steroid taper; refractory pneumonitis; refractory myocarditis or nephritis
| Drug | Dose | Route | Schedule |
|---|---|---|---|
| Hepatitis | |||
| Mycophenolate mofetil | 1 to 2 g a day | Oral | In two divided doses |
| Pneumonitis | |||
| Mycophenolate mofetil | 1 to 1.5 g | Oral | Twice a day; taper with pulmonology advice |
Intravenous immunoglobulin (IVIG) and plasmapheresis
Myasthenia, Guillain-Barré syndrome, encephalitis; refractory pneumonitis
Myasthenia, Guillain-Barré syndrome, encephalitis; refractory pneumonitis
| Drug | Dose | Route | Schedule |
|---|---|---|---|
| Neurological | |||
| IVIG | 2 g/kg (0.4 g/kg/day) | IV | Over 5 days |
| Pneumonitis | |||
| High-dose IVIG | 2 g/kg | IV | Divided over 2 to 5 days |
| Neurological | |||
| Plasmapheresis | — | — | Myasthenia: 5 days; refractory encephalitis: one session every other day, 5 to 7 sessions |
In encephalitis refractory to pulse steroids, rituximab 375 mg/m² weekly for 4 weeks is also an option [2].
Hormone replacement in endocrinopathies
Hypothyroidism, hypophysitis, adrenal insufficiency
Hypothyroidism, hypophysitis, adrenal insufficiency
| Drug | Dose | Route | Schedule |
|---|---|---|---|
| Hypothyroidism | |||
| Levothyroxine | 1.5 to 1.6 µg/kg/day (young and healthy); 25 or 50 µg/day (over 65 or with heart disease) | Oral | Daily |
| Hypophysitis | |||
| Hydrocortisone | 10 to 12 mg/m²/day | Oral | Daily (replacement dose) |
Before starting levothyroxine when concurrent adrenal insufficiency is suspected, check cortisol; teach stress dosing and emergency dexamethasone or hydrocortisone injection, and give a medical alert bracelet [2].
Pyridostigmine
ICI-induced myasthenia gravis (with corticosteroids)
ICI-induced myasthenia gravis (with corticosteroids)
| Drug | Dose | Route | Schedule |
|---|---|---|---|
| Pyridostigmine | Start at 30 mg three times a day; increase gradually to a maximum of 120 mg four times a day | Oral | According to symptoms and tolerance |
As in SITC 2021; in grade 2, prednisone 1 to 1.5 mg/kg/day and stop the ICI [2].
Doses follow the trial protocol, guideline or official drug label (source given in the notes of each regimen). Before prescribing, check blood counts, renal and hepatic function, drug interactions and the patient’s condition, and adjust the dose according to the drug label.
Cytokine release syndrome (CRS) after CAR-T and bispecific antibodies
| Grade | Fever | Hypotension | Hypoxia |
|---|---|---|---|
| 1 | Temperature ≥38 °C | None | None |
| 2 | Temperature ≥38 °C | Not requiring vasopressors | Requiring low-flow nasal cannula (≤6 L/min) or blow-by oxygen |
| 3 | Temperature ≥38 °C | Requiring one vasopressor, with or without vasopressin | Requiring high-flow nasal cannula (above 6 L/min), face mask, non-rebreather mask or Venturi mask |
| 4 | Temperature ≥38 °C | Requiring multiple vasopressors (excluding vasopressin) | Requiring positive pressure (CPAP, BiPAP, intubation and mechanical ventilation) |
The grade is set by the most severe event (hypotension or hypoxia not attributable to another cause); after antipyretics, tocilizumab or corticosteroids, fever is no longer required for grading. Organ toxicities do not affect the CRS grade and are graded separately with CTCAE [4].
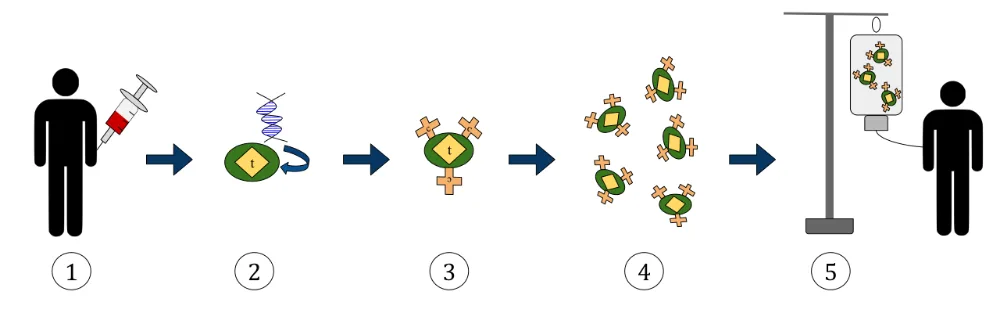
Incidence and timing. In the axicabtagene ciloleucel label, CRS occurred in 93% of patients with large B-cell lymphoma (grade ≥3 in 9%, by the Lee criteria), with a median onset 2 to 3 days after infusion [13]. With the bispecific antibody teclistamab, CRS occurred in 64% (grade 1 in 46%, grade 2 in 18% and grade 3 in 0.2%), mostly during step-up doses, with a median onset 2 days after the last dose [14].
Consensus recommendations. SITC: in adults with grade 2 CRS, tocilizumab can be given, and earlier in older patients or those with comorbidities; if there is no improvement after one dose, add corticosteroids with the second tocilizumab dose, and if no improvement after two doses, consider third-line drugs (anakinra, siltuximab or high-dose methylprednisolone) and reassess for infection [5]. ASCO also treats prolonged or severe CRS with tocilizumab with or without corticosteroids [15]. Do not give CAR-T with active infection or an inflammatory disorder; monitor the patient at least daily for 7 days, keep them near the treatment centre for at least 2 weeks, and advise no driving for 2 weeks [13].
A stepwise approach to CRS
- 1
- 2
- 3
- 4
- 5
5. No response
After one tocilizumab dose: corticosteroids with the second dose; after two doses: anakinra, siltuximab or high-dose methylprednisolone and reassessment for infection [5].
- 6
6. Grades 3 and 4
Intensive care; tocilizumab plus dexamethasone 10 mg three times a day (grade 3) or methylprednisolone 1000 mg daily for 3 days (grade 4); in severe CRS consider an echocardiogram [13].
Neurotoxicity (ICANS) and late neurological toxicity
| Grade | ICE score | Level of consciousness | Seizures | Motor findings and raised intracranial pressure |
|---|---|---|---|---|
| 1 | 7 to 9 | Awakens spontaneously | — | — |
| 2 | 3 to 6 | Awakens to voice | — | — |
| 3 | 0 to 2 | Awakens only to tactile stimulus | Any clinical seizure, focal or generalised, that resolves rapidly, or non-convulsive seizures on EEG that resolve with intervention | Focal oedema on imaging |
| 4 | 0 (unarousable and unable to be assessed) | Unarousable or requires vigorous or repetitive stimuli; stupor or coma | Life-threatening prolonged seizure (more than 5 minutes) or repetitive seizures without return to baseline | Deep focal motor weakness (hemiparesis, paraparesis); diffuse cerebral oedema, decerebrate or decorticate posturing, cranial nerve VI palsy, papilloedema or Cushing's triad |
ICE score (10 points): orientation to year, month, city and hospital (4), naming 3 objects (3), following a command (1), writing a standard sentence (1) and counting backwards from 100 in tens (1). The grade is set by the most severe finding; an awake patient with global aphasia and an ICE of zero is grade 3. Tremor, myoclonus and intracranial haemorrhage are not included in ICANS grading. For children under 12, the CAPD is used [4].
Presentation and timing. The first signs of ICANS are usually tremor, impaired handwriting, mild expressive difficulty (especially naming objects), impaired attention, apraxia and drowsiness [4]. In the axicabtagene label, neurotoxicity occurred in 74 to 87% of patients with large B-cell lymphoma (grade ≥3 in 25 to 31%) with a median onset of 4 to 5 days; 87% of affected patients developed it in the first 7 days and 98% of all cases in the first 8 weeks, but late encephalopathy and fatal cerebral oedema have also been reported [13]. With teclistamab, ICANS occurred in 6% [14].
Treatment principles. Tocilizumab did not resolve ICANS in several trials and may worsen it by raising IL-6 in the cerebrospinal fluid; so in ICANS, managing neurotoxicity takes priority over treating mild CRS, and corticosteroids are the mainstay. Levetiracetam is the drug of choice for seizures, and its prophylaxis can be considered in high-risk patients [5]. ASCO also manages moderate to severe ICANS with corticosteroids and supportive care [15].
Late neurotoxicity with anti-BCMA CAR-T. With ciltacabtagene autoleucel, parkinsonism in 3% (median onset 56 days, often persistent), cranial nerve palsies in 7% (especially cranial nerve VII; median onset 21 days) and Guillain-Barré syndrome (including a fatal case despite IVIG) have been reported; continue neurological monitoring after the acute period [8].
Doses for treating CRS and ICANS (FDA labels for axicabtagene ciloleucel and tocilizumab)
Tocilizumab in CRS
CRS grade 2 and above (or earlier based on clinical judgement)
CRS grade 2 and above (or earlier based on clinical judgement)
| Drug | Dose | Route | Schedule |
|---|---|---|---|
| Tocilizumab | Weight ≥30 kg: 8 mg/kg (maximum 800 mg per dose); weight below 30 kg: 12 mg/kg | IV, 60-minute infusion | If no improvement, repeat at least 8 hours apart |
Corticosteroids in CRS (Lee grading in the label)
According to CRS grade; with tocilizumab from grade 2
According to CRS grade; with tocilizumab from grade 2
| Drug | Dose | Route | Schedule |
|---|---|---|---|
| Grade 1 for more than 3 days | |||
| Dexamethasone | 10 mg | IV | One dose |
| Grade 2 | |||
| Dexamethasone | 10 mg | IV | Once a day |
| Grade 3 | |||
| Dexamethasone | 10 mg | IV | Three times a day |
| Grade 4 | |||
| Methylprednisolone | 1000 mg | IV | Once a day for 3 days; if no improvement, 1000 mg 2 to 3 times a day |
Corticosteroids in ICANS without concurrent CRS
Neurotoxicity; with concurrent CRS, add tocilizumab as in the CRS table
Neurotoxicity; with concurrent CRS, add tocilizumab as in the CRS table
| Drug | Dose | Route | Schedule |
|---|---|---|---|
| Grade 1 | |||
| Dexamethasone | 10 mg | IV | One dose; repeat if no improvement after 2 days |
| Grade 2 | |||
| Dexamethasone | 10 mg | IV | Four times a day |
| Grade 3 | |||
| Methylprednisolone | 1000 mg | IV | Once a day |
| Grade 4 | |||
| Methylprednisolone | 1000 mg | IV | Twice a day; if no improvement, 1000 mg three times a day |
At all grades consider levetiracetam for seizure prophylaxis; from grade 2, continuous cardiac monitoring and pulse oximetry, and intensive care in severe cases. In the label, neurotoxicity severity is graded with CTCAE [13].
Teclistamab premedication and step-up dosing
BCMA×CD3 bispecific antibody in multiple myeloma; reducing the risk of CRS
BCMA×CD3 bispecific antibody in multiple myeloma; reducing the risk of CRS
| Drug | Dose | Route | Schedule |
|---|---|---|---|
| 1 to 3 hours before step-up doses and the first treatment dose | |||
| Dexamethasone | 16 mg | Oral or IV | Before each dose in this phase |
| Same | |||
| Diphenhydramine (or equivalent) | 50 mg | Oral or IV | Before each dose in this phase |
| Paracetamol | 650 to 1000 mg | Oral or IV | Before each dose in this phase |
| Step-up | |||
| Teclistamab | 0.06 mg/kg, then 0.3 mg/kg, then the first treatment dose of 1.5 mg/kg | Subcutaneous | Each dose 2 to 4 days after the previous one (up to 7 days with adverse events) |
Admission for 48 hours after step-up doses 1 and 2; after the first treatment dose, 48 hours of daily monitoring near the treatment centre. Before starting, consider herpes zoster antiviral prophylaxis. After an interruption or CRS with the previous dose, premedication may be needed again [14].
Doses follow the trial protocol, guideline or official drug label (source given in the notes of each regimen). Before prescribing, check blood counts, renal and hepatic function, drug interactions and the patient’s condition, and adjust the dose according to the drug label.
HLH-like syndrome (IEC-HS), cytopenias (ICAHT) and infection after cell therapy
IEC-HS. The ASTCT panel defines this syndrome as an inflammatory syndrome with features of macrophage activation/HLH that is attributable to immune effector cell therapy and is associated with progression or new onset of cytopenias, hyperferritinaemia, coagulopathy with hypofibrinogenaemia and/or raised transaminases; it often appears later, as CRS is resolving. A ferritin above 2 × the upper limit of normal (or the baseline at infusion) or a rapid rise is a prerequisite for diagnosis [6]. Initial treatment is corticosteroids with or without anakinra, and assessing the response for about 48 hours before adding the next drug is recommended; ruxolitinib is second line and etoposide is for life-threatening and refractory cases. Tocilizumab or siltuximab without features of CRS is not recommended for IEC-HS [6]. With ciltacabtagene autoleucel, HLH/MAS occurred in 1% of patients, all in the setting of ongoing or worsening CRS [8].
ICAHT. Haematological toxicity is the most common adverse event after CAR-T and may be profound, prolonged and biphasic [7]. The EHA/EBMT consensus considers G-CSF from day 2 after infusion in high-risk patients (without an increase in severe CRS or ICANS in retrospective studies); more than 80% of patients eventually respond to G-CSF, and in refractory cytopenia after day 14, an infusion of stored autologous stem cells (boost) or a thrombopoietin agonist are options. The CAR-HEMATOTOX score before infusion identifies high-risk patients [7].
Infection prevention. Antiviral and anti-pneumocystis prophylaxis and IVIG replacement in hypogammaglobulinaemia per EHA/EBMT guidelines; fluoroquinolone prophylaxis is not recommended in low-risk patients and can be considered in high-risk patients when neutrophils fall below 500; anti-mould prophylaxis (for example micafungin or posaconazole) at high risk of grade ≥3 ICAHT when neutrophils are below 500, especially with a history of allogeneic transplant, previous aspergillosis or prolonged or high-dose corticosteroids (more than 10 mg dexamethasone); a neutropenic diet is not recommended [7]. Bispecific antibodies can also cause severe and fatal infections [14].
Secondary malignancy. T-cell lymphomas (sometimes CAR-positive) have occurred after anti-CD19 and anti-BCMA CAR-T and may appear a few weeks after infusion; lifelong monitoring is needed [13].
| Criterion | Grade 1 | Grade 2 | Grade 3 | Grade 4 |
|---|---|---|---|---|
| Duration of neutrophils ≤500/µL | Less than 7 days | 7 to 13 days | ≥14 days | Never above 500 |
| Duration of neutrophils ≤100/µL | — | — | ≥7 days | ≥14 days |
Late ICAHT (after day 30) is graded by neutrophil thresholds of ≤1500, ≤1000, ≤500 and ≤100 (measured on at least 2 occasions, or non-transient neutropenia) [7].
Practical and exam points
- In irAEs, ICI dose reduction makes no sense; either continue, hold or stop permanently [2].
- Grade 4 means permanent discontinuation, except endocrinopathies controlled with hormones [1].
- Steroid-refractory ICI hepatitis: mycophenolate, not infliximab [2].
- Refractory colitis (3 to 5 days): infliximab 5 mg/kg at weeks 0, 2 and 6; send HBV, HIV and tuberculosis tests beforehand but do not wait [2].
- Hypophysitis: low TSH with low free T4; replace cortisol before levothyroxine [2].
- Myocarditis: the most fatal irAE; median onset 34 days; methylprednisolone 1 g daily; also assess for myositis and myasthenia [2, 3, 12].
- In ASTCT, CRS is graded by fever + hypotension and/or hypoxia; the hypoxia boundary between grades 2 and 3 is oxygen at 6 L/min [4].
- The ICE score is out of 10; ICE zero in an awake patient with aphasia = grade 3, in an unarousable patient = grade 4 [4].
- Tocilizumab does not treat ICANS; in ICANS, corticosteroids and levetiracetam [5].
- Fever, worsening cytopenias and rising ferritin after CRS resolves: think of IEC-HS; corticosteroids ± anakinra [6].
Key guidelines and studies
Key guidelines and studies
12 itemsManagement of Immune-Related Adverse Events in Patients Treated With Immune Checkpoint Inhibitor Therapy: ASCO Guideline Update
Management of toxicities from immunotherapy: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up
ASTCT Consensus Grading for Cytokine Release Syndrome and Neurologic Toxicity Associated with Immune Effector Cells
Immune-Related Adverse Events Associated with Immune Checkpoint Blockade
Fatal Toxic Effects Associated With Immune Checkpoint Inhibitors
Incidence of Endocrine Dysfunction Following the Use of Different Immune Checkpoint Inhibitor Regimens
2022 ESC Guidelines on cardio-oncology developed in collaboration with the European Hematology Association (EHA), the European Society for Therapeutic Radiology and Oncology (ESTRO) and the International Cardio-Oncology Society (IC-OS)
Final, 10-Year Outcomes with Nivolumab plus Ipilimumab in Advanced Melanoma
Axicabtagene Ciloleucel CAR T-Cell Therapy in Refractory Large B-Cell Lymphoma
Tisagenlecleucel in Children and Young Adults with B-Cell Lymphoblastic Leukemia
Teclistamab in Relapsed or Refractory Multiple Myeloma
Cilta-cel or Standard Care in Lenalidomide-Refractory Multiple Myeloma
Self-assessment questions
A patient on nivolumab + ipilimumab has 6 more stools a day than baseline (grade 2). After 4 days of prednisone 1 mg/kg there is no improvement. Next step?
Corticosteroid-refractory colitis (no response in 3 to 5 days): infliximab 5 mg/kg at weeks 0, 2 and 6; check HBV, HIV and tuberculosis beforehand (without delaying treatment), and because grade 2 has lasted more than 5 days, endoscopy with biopsy and exclusion of Clostridioides difficile and CMV are needed. If symptoms persist after the second infliximab dose, vedolizumab 300 mg at weeks 0, 2 and 6 [2].
A patient on pembrolizumab has an ALT 8 times the upper limit of normal with no improvement after 2 weeks of methylprednisolone. Why is infliximab not a suitable option?
Because of the risk of hepatotoxicity, infliximab is not used in ICI hepatitis; mycophenolate mofetil 1 to 2 g a day (in two doses) is the option, and with no response after 10 to 14 days, a liver biopsy and exclusion of CMV; tacrolimus and ATG are other options [2].
A patient with headache and tiredness, sodium 128, low TSH and low free T4 after ipilimumab. Diagnosis and order of treatment?
A low TSH with low free T4 points to hypophysitis; measure ACTH and morning cortisol and then the other axes. In symptomatic acute hypophysitis, the ICI is held and corticosteroids started, then hydrocortisone replacement (10 to 12 mg/m²/day) with stress-dose education; cortisol replacement must come before levothyroxine [2]. Ipilimumab carries a higher risk of hypophysitis than PD-1 inhibitors [11].
Four weeks after starting an ICI, the patient's troponin has risen but the ejection fraction is normal. Is a normal ejection fraction reassuring?
No; in a multicentre registry, 38% of major adverse cardiac events occurred with a normal ejection fraction, and troponin T ≥1.5 ng/mL increased the risk fourfold [12]. Admit the patient, assess with cardiac MRI, ECG and troponin, and start methylprednisolone 1000 mg daily as soon as possible; also assess for myositis and myasthenia [2].
Day 2 after CAR-T: temperature 39.2 °C, blood pressure stabilised with fluids, and oxygen at 4 L by nasal cannula. What is the CRS grade (ASTCT) and the treatment?
Grade 2 (hypotension not requiring vasopressors and hypoxia on low-flow cannula ≤6 L) [4]. After investigating and treating infection, tocilizumab 8 mg/kg IV over 60 minutes (maximum 800 mg) and, according to the axicabtagene label, dexamethasone 10 mg daily, with continuous cardiac monitoring and pulse oximetry [13, 16].
After CAR-T the patient wakes only to tactile stimulus and has an ICE of 2, without seizures. What is the ICANS grade and treatment?
Three weeks after CAR-T, CRS has resolved but the patient has worsening pancytopenia, rising ferritin, low fibrinogen and raised transaminases. Diagnosis and treatment?
IEC-HS (HLH-like syndrome after cell therapy), which often appears as CRS resolves; after excluding other causes (such as infection), corticosteroids with or without anakinra, assessing the response at about 48 hours; ruxolitinib second line and etoposide for life-threatening and refractory cases. Tocilizumab without features of CRS is not recommended [6].
A patient 18 days after CAR-T still has neutrophils below 500 and has never been above 500. What is the ICAHT grade and action?
Neutrophils ≤500 for ≥14 days is grade 3 (if never above 500 by day 30, grade 4) [7]. Therapeutic G-CSF, anti-mould prophylaxis in a high-risk patient, investigation of other causes (including HLH-like syndrome) and, with no response to G-CSF after day 14, an infusion of stored autologous stem cells if available [7].
References
16 referencesShow all references, 5 with a study cardClose the reference list
Numbers in the text, such as [1], refer to these sources. Sources with a “Study card” button are summarised in the site’s evidence library.
- 1
- 2
- 3
- 4
- 5
- 6
- 7
- 8
- 9Management of toxicities from immunotherapy: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up
- 10Combined Nivolumab and Ipilimumab or Monotherapy in Untreated Melanoma
- 11Incidence of Endocrine Dysfunction Following the Use of Different Immune Checkpoint Inhibitor Regimens: A Systematic Review and Meta-analysis
- 12
- 13
- 14
- 15
- 16
This page is based on reputable scientific sources and was last updated on 28 October 2026. The content of this website is for educational and informational purposes only and does not replace consultation, diagnosis or treatment by a specialist physician. Consult your treating physician about any treatment decision.
Printed from the website; the full and up-to-date version: https://drdabiri.com/en/learn/immunotherapy-cart-toxicity/